
Introduction
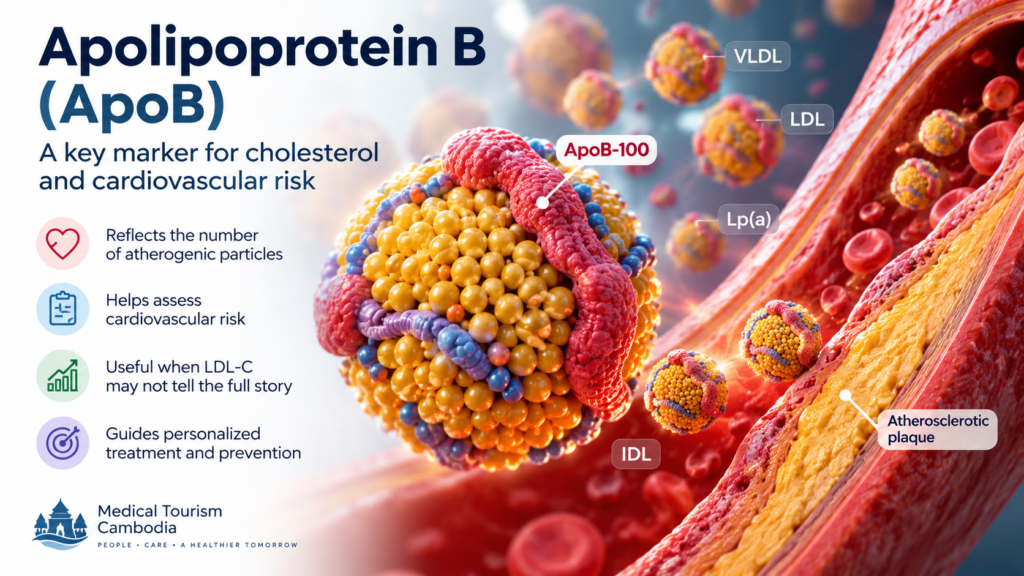
Apolipoprotein B (ApoB) is an important blood biomarker used to assess the risk of atherosclerotic cardiovascular disease (ASCVD), including coronary artery disease, myocardial infarction, and ischemic stroke.
Traditionally, clinicians evaluate cardiovascular risk using a standard lipid profile, which includes total cholesterol, low-density lipoprotein cholesterol (LDL-C), high-density lipoprotein cholesterol (HDL-C), and triglycerides. However, these measurements do not always accurately reflect the number of cholesterol-carrying particles capable of entering the arterial wall and contributing to atherosclerosis.
ApoB provides additional information by estimating the total number of atherogenic lipoprotein particles circulating in the blood. It can be particularly useful in patients with diabetes, obesity, metabolic syndrome, elevated triglycerides, or established cardiovascular disease.
The 2026 ACC/AHA multisociety dyslipidemia guideline recognizes ApoB measurement as a useful tool for identifying residual cardiovascular risk and guiding treatment in selected patients, particularly when LDL-C and non-HDL-C treatment goals have already been achieved.
1. What Is Apolipoprotein B?
Apolipoprotein B is a structural protein found on atherogenic lipoproteins—particles that can contribute to cholesterol accumulation in arterial walls.
There are two main forms:
- ApoB-100: Produced primarily by the liver and present in very-low-density lipoprotein (VLDL), intermediate-density lipoprotein (IDL), LDL, and lipoprotein(a) [Lp(a)].
- ApoB-48: Produced in the intestine and found in chylomicrons and their remnants.
ApoB-100 is the principal form measured in routine clinical ApoB testing.
Each circulating atherogenic particle contains one molecule of ApoB. Consequently, the blood ApoB concentration provides an estimate of the number of atherogenic particles rather than simply measuring the amount of cholesterol they carry.
This distinction is clinically important because two people may have the same LDL-C concentration but different numbers of circulating atherogenic particles.
2. Why Is ApoB Important?
Atherosclerosis develops when atherogenic lipoproteins enter and become retained within the arterial wall, initiating inflammation and plaque formation.
ApoB-containing lipoproteins include:
- LDL particles
- VLDL particles
- IDL particles
- Chylomicron remnants
- Lipoprotein(a)
The risk associated with these particles depends on their concentration, exposure over time, and other patient-specific cardiovascular risk factors.
ApoB helps clinicians assess the burden of these particles more directly than LDL-C alone.
ApoB versus LDL-C
LDL-C measures the amount of cholesterol carried within LDL particles. ApoB estimates the number of circulating atherogenic particles.
When particles contain relatively little cholesterol, LDL-C may appear satisfactory even though the number of atherogenic particles remains high. This is known as ApoB–LDL-C discordance.
In these circumstances, ApoB can reveal residual cardiovascular risk that may not be apparent from the standard lipid profile.
3. Who Should Consider an ApoB Test?
ApoB testing is not necessary for every patient. It is most useful when the result may change cardiovascular risk assessment or treatment decisions.
Consider measuring ApoB in the following situations:
1. Type 2 diabetes mellitus
Patients with diabetes may have increased numbers of small, cholesterol-depleted LDL particles and elevated triglyceride-rich lipoproteins.
2. Hypertriglyceridemia
When triglycerides are elevated, LDL-C may underestimate the total burden of atherogenic particles. ApoB can provide additional information.
3. Metabolic syndrome or obesity
Insulin resistance, abdominal obesity, elevated triglycerides, and low HDL-C frequently occur with increased ApoB particle concentrations.
4. Established ASCVD
Patients with previous myocardial infarction, ischemic stroke, or peripheral arterial disease may benefit from ApoB assessment when evaluating residual risk despite treatment.
5. LDL-C at goal but persistent concern about cardiovascular risk
ApoB may help identify patients whose particle burden remains elevated despite apparently satisfactory LDL-C and non-HDL-C values.
6. Suspected inherited lipid disorders
ApoB can assist in characterizing certain lipid abnormalities, including familial combined hyperlipidemia.
The 2026 ACC/AHA guideline considers ApoB measurement reasonable in adults receiving lipid-lowering therapy, particularly those with ASCVD, cardiovascular-kidney-metabolic syndrome, type 2 diabetes, or elevated triglycerides, once LDL-C and/or non-HDL-C goals have been achieved. It may also be reasonable in selected untreated adults to improve risk assessment.
4. ApoB Compared With LDL-C, Non-HDL-C, and Lipoprotein(a)
| Test | What it measures | Main clinical value |
|---|---|---|
| LDL-C | Cholesterol carried in LDL | Established treatment marker and target |
| Non-HDL-C | Cholesterol in all non-HDL lipoproteins | Captures cholesterol carried by LDL and triglyceride-rich atherogenic particles |
| ApoB | Concentration of ApoB-containing particles | Estimates total atherogenic particle burden |
| Lipoprotein(a), or Lp(a) | Concentration of a genetically influenced, LDL-like lipoprotein | Identifies an additional inherited cardiovascular risk factor |
These tests provide complementary information. ApoB does not replace LDL-C or non-HDL-C, and Lp(a) should not be confused with ApoB.
The 2026 ACC/AHA guideline also recommends measuring Lp(a) at least once in adulthood to improve cardiovascular risk assessment.
5. How Is ApoB Measured?
ApoB is measured using a blood test, usually through an immunochemical laboratory assay.
The result is commonly reported in milligrams per deciliter (mg/dL) or grams per liter (g/L).
For example:
- ApoB 70 mg/dL = 0.70 g/L
- ApoB 90 mg/dL = 0.90 g/L
- ApoB 120 mg/dL = 1.20 g/L
Fasting is generally not required specifically for ApoB measurement. However, a fasting lipid profile may be appropriate when evaluating substantial hypertriglyceridemia or when requested by the treating clinician.
ApoB should be interpreted alongside LDL-C, non-HDL-C, triglycerides, medical history, current treatment, and overall cardiovascular risk.
6. What Is a Normal ApoB Level?
A laboratory reference interval is not the same as a treatment goal.
There is no single ApoB concentration that is appropriate for every patient. Interpretation depends on the patient’s cardiovascular risk, presence of established disease, lipid profile, and treatment status.
The 2026 ACC/AHA guideline emphasizes risk-based management and the use of ApoB to guide selected treatment decisions. It does not establish one universal ApoB target for all adults.
For context, European dyslipidemia guidance has historically used the following secondary ApoB goals:
| Cardiovascular risk category | ApoB goal commonly used in European guidance |
|---|---|
| Very high risk | Less than 65 mg/dL |
| High risk | Less than 80 mg/dL |
| Moderate risk | Less than 100 mg/dL |
These are European risk-based goals, not universal laboratory reference limits or targets mandated for every patient by the 2026 US guideline. The applicable national guideline and individual clinical circumstances should determine the treatment goal.
An ApoB concentration of 100 mg/dL, for example, may have different implications in a healthy adult without major risk factors compared with a patient who has had a myocardial infarction.
7. How Should Clinicians Interpret an Elevated ApoB?
An elevated ApoB concentration suggests an increased burden of atherogenic lipoprotein particles and may indicate greater long-term ASCVD risk.
Clinical interpretation should include the following steps:
Step 1: Assess the complete lipid profile.
Review LDL-C, non-HDL-C, triglycerides, and HDL-C. Consider whether the LDL-C result accurately reflects the patient’s overall atherogenic particle burden.
Step 2: Evaluate cardiovascular risk.
Consider established ASCVD, diabetes, hypertension, chronic kidney disease, smoking, family history of premature cardiovascular disease, and other relevant risk factors.
Step 3: Look for ApoB–LDL-C discordance.
A patient with LDL-C at goal but persistently elevated ApoB may have residual atherogenic particle risk.
Step 4: Review secondary and metabolic contributors.
Assess for insulin resistance, uncontrolled diabetes, hypothyroidism, excess alcohol intake, dietary factors, kidney disease, and medications that may contribute to dyslipidemia, as clinically appropriate.
Step 5: Optimize treatment according to overall risk.
Treatment decisions should be based on the complete clinical picture, not on ApoB alone.
8. How Can ApoB Be Lowered?
ApoB can often be reduced by lowering the concentration of atherogenic lipoproteins. Treatment depends on the patient’s baseline lipid profile, cardiovascular risk, comorbidities, and response to previous therapy.
Lifestyle interventions
Recommended measures include:
- Follow a heart-healthy dietary pattern rich in vegetables, fruits, legumes, whole grains, nuts, and appropriate sources of unsaturated fats.
- Reduce saturated fat and avoid industrial trans fats.
- Limit refined carbohydrates and added sugars, especially when triglycerides are elevated.
- Achieve and maintain a healthy body weight.
- Exercise regularly, aiming for at least 150 minutes of moderate-intensity aerobic activity weekly when medically appropriate.
- Avoid tobacco and manage alcohol intake.
- Optimize diabetes, blood pressure, and other cardiovascular risk factors.
Lipid-lowering medications
Statins
Statins are generally the first-line pharmacological treatment when indicated. They reduce LDL-C and ApoB-containing lipoproteins and have strong evidence for preventing cardiovascular events.
Ezetimibe
Ezetimibe reduces intestinal cholesterol absorption and can be added when further LDL-C lowering is needed.
Bempedoic acid
This medication lowers LDL-C and can be useful in selected patients, including some patients who cannot tolerate recommended statin regimens.
PCSK9 monoclonal antibodies
Alirocumab and evolocumab substantially lower LDL-C and ApoB-containing lipoproteins and are used in selected high-risk patients.
Inclisiran
Inclisiran reduces hepatic PCSK9 production and lowers LDL-C. Its role in clinical management depends on patient-specific indications, access, and the applicable guideline.
Triglyceride-directed treatment
When triglycerides are elevated, address secondary causes and optimize lifestyle and LDL-lowering treatment. Selected high-risk patients may benefit from additional triglyceride-directed therapy, such as icosapent ethyl, when they meet the relevant clinical criteria.
The choice of medication should be based on evidence for cardiovascular risk reduction, patient characteristics, safety, cost, and local availability. The purpose of ApoB measurement is to improve risk assessment and guide treatment—not to prescribe medication solely to reach an isolated laboratory number.
9. ApoB in the 2026 Dyslipidemia Guidelines
The 2026 ACC/AHA multisociety guideline expands the role of atherogenic lipoprotein assessment beyond LDL-C alone.
Important recommendations include:
- Continue to prioritize LDL-C lowering and risk-based lipid management.
- Use non-HDL-C to assess cholesterol carried by atherogenic lipoproteins beyond LDL.
- Consider ApoB testing in selected patients, particularly those with diabetes, cardiovascular-kidney-metabolic syndrome, elevated triglycerides, or established ASCVD.
- Consider further treatment intensification when ApoB remains elevated despite achieving LDL-C and/or non-HDL-C goals.
- Use ApoB selectively in untreated adults when it could improve risk assessment or help characterize a lipid disorder.
- Measure Lp(a) at least once in adulthood as part of comprehensive cardiovascular risk assessment.
These recommendations support a more individualized approach to cardiovascular prevention. ApoB complements established risk assessment and lipid targets rather than replacing them.
10. Key Clinical Takeaways
- ApoB estimates the number of circulating atherogenic lipoprotein particles.
- LDL-C measures cholesterol mass, not the number of LDL particles.
- ApoB is particularly useful in selected patients with diabetes, hypertriglyceridemia, metabolic syndrome, or established ASCVD.
- An elevated ApoB despite an LDL-C at goal may indicate residual atherogenic risk.
- There is no single ApoB treatment target suitable for every patient.
- Treatment should address overall cardiovascular risk, with lifestyle measures and evidence-based lipid-lowering medication when indicated.
- ApoB should complement, not replace, LDL-C, non-HDL-C, and comprehensive cardiovascular risk assessment.
Conclusion
Apolipoprotein B is a valuable biomarker for assessing atherogenic lipoprotein particle burden and refining cardiovascular risk assessment in selected patients. It is particularly useful when LDL-C may not fully reflect the number of circulating atherogenic particles, as often occurs in diabetes, hypertriglyceridemia, and metabolic syndrome.
The 2026 ACC/AHA multisociety dyslipidemia guideline supports selective ApoB measurement to identify residual risk and help guide lipid-lowering treatment. Integrating ApoB with LDL-C, non-HDL-C, Lp(a), and the patient’s overall cardiovascular risk can help clinicians make more informed decisions about prevention and treatment.
Medical disclaimer: This article is for educational purposes and does not replace an individual medical consultation. Decisions about laboratory testing and lipid-lowering therapy should be made with a qualified healthcare professional.
Frequently Asked Questions (FAQ)
1. What is ApoB in a blood test?
ApoB is a protein found on atherogenic lipoproteins, including LDL, VLDL, IDL, and Lp(a). Its blood concentration estimates the number of circulating atherogenic particles.
2. Is ApoB more accurate than LDL-C?
ApoB may better reflect atherogenic particle burden when ApoB and LDL-C results disagree. This is particularly relevant in patients with diabetes, elevated triglycerides, or metabolic syndrome. Both tests remain clinically useful.
3. What is an ideal ApoB level?
The appropriate level depends on cardiovascular risk. European guidance has used secondary goals below 65 mg/dL for very-high-risk patients, below 80 mg/dL for high-risk patients, and below 100 mg/dL for moderate-risk patients. These are not universal targets for all adults.
4. Should everyone have an ApoB test?
No. A standard lipid profile remains essential. ApoB is most useful when the result could change risk assessment or treatment decisions, particularly in selected high-risk patients or those with elevated triglycerides.
5. Do I need to fast before an ApoB test?
Fasting is generally unnecessary for ApoB measurement itself. Your clinician may nevertheless request a fasting lipid profile in certain situations, particularly with significant hypertriglyceridemia.
6. Can ApoB be high when LDL-C is normal?
Yes. The cholesterol content of individual particles varies. A patient can have a relatively satisfactory LDL-C concentration but an elevated number of atherogenic particles, resulting in a higher ApoB concentration.
7. Does high ApoB mean I will have a heart attack?
No. Elevated ApoB does not predict with certainty that an individual will develop cardiovascular disease. It indicates a potentially important risk factor that should be interpreted alongside age, blood pressure, diabetes, smoking, family history, and other clinical findings.
8. Can diet and exercise lower ApoB?
Yes. Improving diet quality, losing excess weight, exercising regularly, and controlling metabolic risk factors can reduce ApoB in many patients. The degree of improvement depends on the underlying lipid disorder and individual response.
9. Which medications lower ApoB?
Statins are commonly the first-line medications when pharmacological treatment is indicated. Ezetimibe, bempedoic acid, PCSK9 inhibitors, and other therapies may be added according to cardiovascular risk, lipid response, and treatment indications.
10. Is ApoB the same as lipoprotein(a), or Lp(a)?
No. ApoB is a protein present on several types of atherogenic lipoproteins. Lp(a) is a specific LDL-like lipoprotein that contains ApoB-100 linked to apolipoprotein(a). Both can contribute to cardiovascular risk, but they measure different things.
11. Does a high ApoB level require medication?
Not automatically. The decision depends on the person’s overall cardiovascular risk, lipid profile, medical history, and whether recommended LDL-C and non-HDL-C goals have been achieved. ApoB may help refine that decision.
12. How often should ApoB be checked?
There is no single testing interval for everyone. Repeat measurement may be useful after a treatment change or when reassessing residual risk, depending on the clinical situation and the treating clinician’s judgment.
References
- Blumenthal RS, Morris PB, and colleagues. 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia. Circulation. 2026. doi:10.1161/CIR.0000000000001423. https://doi.org/10.1161/CIR.0000000000001423
- American Heart Association. 2026 Guideline on the Management of Dyslipidemia: Top Things to Know. Updated March 13, 2026. https://professional.heart.org/en/science-news/2026-guideline-on-the-management-of-dyslipidemia/top-things-to-know
- Mach F, Baigent C, Catapano AL, et al. 2019 ESC/EAS Guidelines for the management of dyslipidaemias: lipid modification to reduce cardiovascular risk. European Heart Journal. 2020;41(1):111–188. doi:10.1093/eurheartj/ehz455.
- Ference BA, Ginsberg HN, Graham I, et al. Low-density lipoproteins cause atherosclerotic cardiovascular disease. European Heart Journal. 2017;38(32):2459–2472. doi:10.1093/eurheartj/ehx144.
- Sniderman AD, Thanassoulis G, Glavinovic T, et al. Apolipoprotein B particles and cardiovascular disease: a narrative review. JAMA Cardiology. 2019;4(12):1287–1295. doi:10.1001/jamacardio.2019.3780.
- Grundy SM, Stone NJ, Bailey AL, et al. 2018 AHA/ACC/AACVPR/AAPA/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Blood Cholesterol. Circulation. 2019;139–e1143. doi:10.1161/CIR.0000000000000625. This guideline has been superseded by the 2026 US multisociety guideline.
For clinical decisions, consult the full current guideline and applicable national recommendations.