
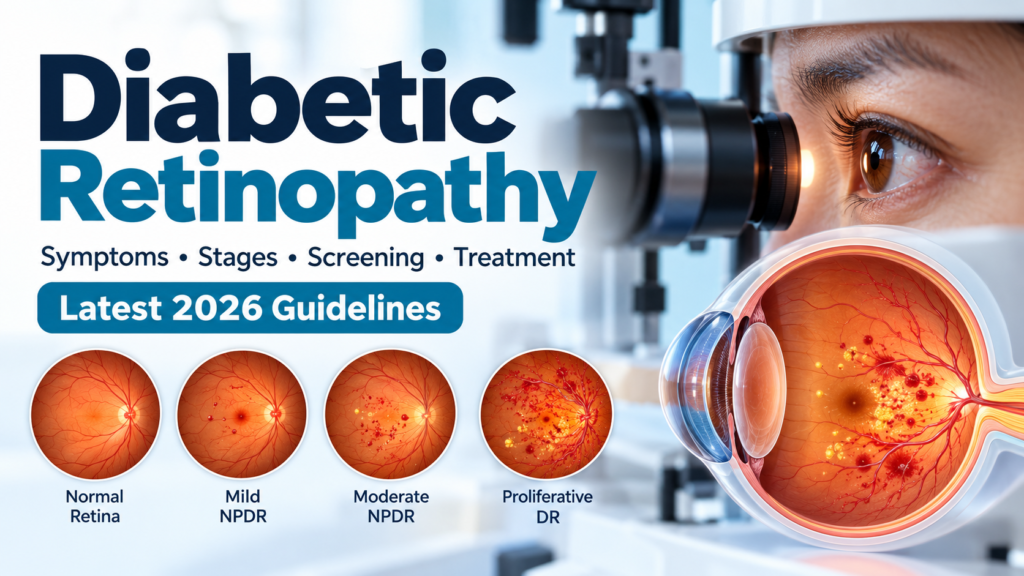
Diabetic retinopathy (DR) is one of the most important complications of diabetes and a major cause of preventable visual impairment. It develops when long-term high blood glucose damages the small blood vessels supplying the retina—the light-sensitive tissue at the back of the eye.
The disease can progress silently for years, and significant retinal damage may occur before a person notices any change in vision. Fortunately, regular screening, good control of diabetes and cardiovascular risk factors, and modern treatments such as intravitreal anti-VEGF therapy and laser photocoagulation can substantially reduce the risk of severe vision loss. DOI
This article reflects the ADA Standards of Care in Diabetes—2026 and current ophthalmology evidence.
What Is Diabetic Retinopathy?
Diabetic retinopathy is a diabetes-related neurovascular disease of the retina.
Persistent hyperglycemia causes biochemical and vascular abnormalities within retinal blood vessels. These changes can result in:
- Microaneurysms
- Retinal hemorrhages
- Capillary closure and retinal ischemia
- Increased vascular permeability
- Retinal edema
- Hard exudates
- Abnormal new blood vessel formation
When abnormal new vessels develop, the disease has progressed to proliferative diabetic retinopathy (PDR). Fluid accumulation in or around the macula can cause diabetic macular edema (DME), which is an important cause of visual impairment. Diabetes Journals
Types and Stages of Diabetic Retinopathy
Diabetic retinopathy is broadly divided into:
- Nonproliferative diabetic retinopathy (NPDR)
- Proliferative diabetic retinopathy (PDR)
Diabetic macular edema can occur at different stages and may coexist with either NPDR or PDR.
1. Mild NPDR
The earliest clinical stage is usually characterized by microaneurysms.
Patients generally have no symptoms.
At this stage, the main approach is:
- Optimize glucose management
- Control blood pressure
- Manage lipids
- Continue appropriate retinal surveillance
2. Moderate NPDR
More extensive retinal vascular abnormalities may develop, including:
- Increasing retinal hemorrhages
- Microaneurysms
- Hard exudates
- Cotton-wool spots
- Venous abnormalities
- Intraretinal microvascular abnormalities
Moderate NPDR is clinically important because it indicates a greater risk of progression toward proliferative disease.
The ADA recommends prompt referral to an experienced ophthalmologist for moderate or worse NPDR. DOI
3. Severe NPDR
Severe NPDR represents extensive retinal ischemia and carries a substantial risk of progression to PDR.
The classic clinical assessment may use the 4-2-1 rule:
- Retinal hemorrhages/microaneurysms in all 4 quadrants
- Venous beading in ≥2 quadrants
- IRMA in ≥1 quadrant
Severe NPDR requires close ophthalmologic monitoring and consideration of treatment depending on the individual clinical situation.
4. Proliferative Diabetic Retinopathy
PDR develops when retinal ischemia stimulates the release of angiogenic factors, particularly vascular endothelial growth factor (VEGF).
Fragile new blood vessels can grow on the retina or optic disc.
These vessels can bleed and cause:
- Vitreous hemorrhage
- Fibrovascular proliferation
- Tractional retinal detachment
- Severe visual loss
PDR is a sight-threatening condition requiring prompt specialist management.
Treatment may include:
- Panretinal photocoagulation
- Intravitreal anti-VEGF therapy
- Vitrectomy in selected advanced cases
The 2026 ADA Standards recommend panretinal laser photocoagulation for high-risk PDR and recognize intravitreal anti-VEGF therapy as an effective alternative for appropriate patients. DOI
Diabetic Macular Edema
Diabetic macular edema (DME) occurs when abnormal retinal blood vessels leak fluid into the macula.
The macula is responsible for detailed central vision, so edema in this region can cause:
- Blurred central vision
- Difficulty reading
- Difficulty recognizing faces
- Distorted vision
- Reduced visual acuity
DME may occur at any stage of diabetic retinopathy.
How is DME diagnosed?
Important investigations include:
- Dilated retinal examination
- Fundus photography
- Optical coherence tomography (OCT)
- Fluorescein angiography in selected cases
OCT is particularly useful for detecting and monitoring retinal thickening and fluid. Current clinical practice guidelines consistently support OCT as an important tool in DME diagnosis and follow-up. PubMed
What Causes Diabetic Retinopathy?
The most important underlying factor is chronic hyperglycemia.
Long-term elevated glucose contributes to:
- Oxidative stress
- Advanced glycation end products
- Endothelial dysfunction
- Inflammation
- Pericyte loss
- Breakdown of the blood-retinal barrier
- Retinal capillary closure
- Retinal ischemia
- Increased VEGF production
Over time, these processes damage retinal microcirculation and neural tissue.
Risk Factors for Diabetic Retinopathy
The major risk factors include:
1. Duration of diabetes
The longer a person has diabetes, the greater the cumulative risk.
2. Poor glycemic control
Higher and prolonged HbA1c levels are strongly associated with development and progression of retinopathy.
3. Hypertension
High blood pressure accelerates retinal vascular injury.
4. Dyslipidemia
Abnormal lipid levels are associated with retinal disease and may contribute to hard exudate formation and progression.
5. Diabetic kidney disease
Nephropathy is associated with a higher risk of diabetic retinopathy.
6. Pregnancy in people with preexisting diabetes
Pregnancy can accelerate preexisting diabetic retinopathy, particularly when retinopathy is already present.
7. Rapid improvement in glycemia
Rapid reductions in HbA1c can occasionally be associated with early worsening of diabetic retinopathy, particularly in people with preexisting advanced disease. Therefore, patients with significant retinopathy should have appropriate ophthalmologic assessment when intensive glucose-lowering therapy is initiated. Diabetes Journals
Symptoms of Diabetic Retinopathy
Early diabetic retinopathy is often asymptomatic.
As the disease progresses, patients may develop:
- Blurred vision
- Difficulty reading
- Fluctuating vision
- Dark spots or floaters
- Shadows or areas of missing vision
- Distorted vision
- Poor night vision
- Sudden loss of vision
A sudden increase in floaters, a curtain-like shadow, or sudden visual loss can indicate vitreous hemorrhage or retinal detachment and requires urgent ophthalmologic assessment.
Why Screening Is So Important
One of the most important facts about diabetic retinopathy is:
You can have advanced diabetic retinopathy without noticing symptoms.
Therefore, waiting until vision becomes blurred is not an appropriate screening strategy.
Early detection allows clinicians to:
- Identify retinal disease before severe vision loss
- Monitor progression
- Treat DME
- Treat high-risk PDR
- Reduce the risk of irreversible visual impairment
Recommended Eye Screening
According to the ADA Standards of Care 2026:
Type 1 diabetes
Adults with type 1 diabetes should have an initial comprehensive dilated eye examination approximately 5 years after diabetes onset. DOI
Type 2 diabetes
People with type 2 diabetes should have a comprehensive dilated eye examination at the time of diagnosis, because retinopathy may already be present when diabetes is first recognized. DOI
If previous examinations are normal
If one or more annual examinations show no retinopathy and glycemic indicators are within the target range, screening every 1–2 years may be considered.
If any diabetic retinopathy is present, retinal examinations should generally occur at least annually, with more frequent examinations when disease is progressing or sight-threatening. DOI
Retinal Photography and Artificial Intelligence
Retinal photography can expand access to diabetic retinopathy screening, particularly where ophthalmologists are limited.
The 2026 ADA Standards recognize:
- Retinal photography with remote expert interpretation
- Appropriate FDA-authorized AI-based screening systems
as acceptable strategies to improve access to screening.
However, abnormal screening results require an appropriate pathway for comprehensive eye examination and specialist care. DOI
AI screening should therefore be viewed as a screening and triage tool, not a replacement for specialist ophthalmologic care when disease is detected.
Diabetic Retinopathy During Pregnancy
Women with preexisting type 1 or type 2 diabetes should receive eye assessment before pregnancy and during early pregnancy.
The ADA recommends:
- Eye examination before pregnancy when possible
- Examination during the first trimester
- Additional examinations during pregnancy depending on the severity of retinopathy
- Continued monitoring postpartum when clinically indicated
This is different from gestational diabetes, which by itself does not generally require diabetic retinopathy screening during pregnancy because it does not appear to increase the risk of diabetic retinopathy. Diabetes Journals
Treatment decisions during pregnancy require collaboration between ophthalmology and the pregnancy/diabetes care team.
Prevention and Medical Management
The best treatment for diabetic retinopathy begins with preventing progression.
1. Optimize blood glucose
Good glycemic control can reduce the risk of developing and progressing diabetic retinopathy.
The goal should be individualized according to:
- Age
- Diabetes duration
- Comorbidities
- Hypoglycemia risk
- Pregnancy status
- Life expectancy
- Patient preferences
The ADA recommends strategies that help patients achieve appropriate glycemic goals to reduce or slow diabetic retinopathy. DOI
2. Control blood pressure
Hypertension increases the risk of retinal vascular damage.
Appropriate blood pressure management is therefore an important component of diabetic retinopathy prevention.
3. Manage cholesterol and cardiovascular risk
Lipid management is also important.
The 2026 ADA Standards recommend achieving appropriate lipid goals to reduce or slow progression of diabetic retinopathy. DOI
Interestingly, evidence also suggests that fenofibrate may have a role in slowing diabetic retinopathy progression in selected people with diabetes, although it should not be considered a substitute for standard lipid management or ophthalmologic treatment. PubMed Central (PMC)
Treatment of Diabetic Retinopathy
Treatment depends on:
- Severity of retinopathy
- Presence and location of DME
- Visual acuity
- Retinal ischemia
- Presence of neovascularization
- Vitreous hemorrhage
- Tractional retinal detachment
Anti-VEGF Therapy
Intravitreal anti-VEGF medications have transformed the treatment of diabetic retinal disease.
They reduce abnormal vascular permeability and VEGF-driven neovascularization.
They are particularly important for:
- Center-involving DME with visual impairment
- Selected PDR
- Some cases of severe diabetic retinal disease
The 2026 ADA Standards recommend intravitreal anti-VEGF therapy as first-line treatment for most eyes with center-involving DME that impairs visual acuity. DOI
Depending on the clinical situation, anti-VEGF agents may include drugs such as:
- Aflibercept
- Ranibizumab
- Faricimab
- Bevacizumab, commonly used off-label in many settings
Treatment usually requires repeated injections and regular OCT/visual assessments.
Panretinal Photocoagulation
Panretinal photocoagulation (PRP) uses laser treatment to reduce ischemic retinal tissue and decrease the stimulus for abnormal neovascularization.
PRP remains an important treatment for:
- High-risk PDR
- Selected severe NPDR
The ADA 2026 guideline continues to recommend PRP to reduce the risk of vision loss in high-risk PDR. DOI
Laser Treatment for Diabetic Macular Edema
Focal/grid laser photocoagulation has historically been an important treatment for DME.
Today, anti-VEGF therapy is generally preferred for most patients with center-involving DME and impaired vision.
Laser may still have a role in:
- Selected non-center-involving DME
- Persistent DME
- Patients who are not candidates for anti-VEGF therapy
The ADA recognizes focal/grid laser as a reasonable treatment for persistent DME despite anti-VEGF therapy or when anti-VEGF is unsuitable. DOI
Intravitreal Corticosteroids
Intravitreal corticosteroids can reduce retinal inflammation and vascular permeability.
They may be considered in selected patients with persistent DME, particularly when response to anti-VEGF therapy is inadequate or anti-VEGF therapy is unsuitable.
Potential adverse effects include:
- Increased intraocular pressure
- Cataract formation
- Glaucoma-related complications
Therefore, patient selection and ophthalmologic monitoring are essential.
Vitrectomy
Pars plana vitrectomy may be necessary for advanced complications such as:
- Non-clearing vitreous hemorrhage
- Tractional retinal detachment involving or threatening the macula
- Severe fibrovascular proliferation
- Selected combined tractional/rhegmatogenous retinal detachments
Surgery is generally performed by a vitreoretinal specialist.
Can Diabetic Retinopathy Be Reversed?
In some patients, treatment can produce substantial improvement in retinal disease and vision.
However, diabetic retinopathy should generally be considered a chronic disease requiring lifelong monitoring.
Even after successful laser or injection therapy, retinopathy can recur or progress.
Therefore:
Treatment does not eliminate the need for diabetes control and regular eye examinations.
Can Good Diabetes Control Prevent Blindness?
Good diabetes management can significantly reduce the risk of diabetic retinopathy and slow its progression.
However, good HbA1c alone does not eliminate the risk.
Patients should also manage:
- Blood pressure
- Lipids
- Kidney disease
- Smoking
- Weight
- Cardiovascular risk
The ADA specifically recommends optimizing glycemia, blood pressure, and lipids to reduce the risk or progression of diabetic retinopathy. DOI
When Should a Patient Seek Urgent Eye Care?
Immediate ophthalmologic assessment is warranted for symptoms such as:
- Sudden loss of vision
- Sudden appearance of many floaters
- Flashes of light
- A curtain or shadow over part of the visual field
- Sudden severe distortion of vision
- New significant visual impairment
These symptoms may indicate vitreous hemorrhage, retinal detachment, or another sight-threatening condition.
Key Take-Home Messages
- Diabetic retinopathy may be asymptomatic in its early stages.
- Every person with diabetes needs appropriate retinal screening.
- Type 2 diabetes requires an eye examination at diagnosis.
- Type 1 diabetes generally requires the first comprehensive eye examination about 5 years after onset.
- Good glucose, blood pressure, and lipid control can reduce progression.
- DME and moderate-or-worse NPDR require timely ophthalmology referral.
- Anti-VEGF injections are a major treatment for vision-threatening DME and selected PDR.
- Panretinal laser remains an important treatment for high-risk PDR.
- Advanced disease may require vitrectomy.
- Early detection and treatment can prevent many cases of severe diabetes-related vision loss.
Frequently Asked Questions
1. Does everyone with diabetes develop diabetic retinopathy?
No. The risk varies according to diabetes duration, glycemic control, blood pressure, lipid levels, kidney disease and other factors.
However, everyone with diabetes should undergo appropriate screening.
2. Can diabetic retinopathy occur when blood sugar is only moderately elevated?
Yes. Risk is related to cumulative glycemic exposure and other risk factors. A person can develop retinopathy even without extremely high glucose levels.
3. Can diabetic retinopathy cause blindness?
Yes. Advanced PDR, severe DME, vitreous hemorrhage and tractional retinal detachment can cause severe or permanent visual impairment.
4. Does blurred vision always mean diabetic retinopathy?
No. Blurred vision can have many causes, including cataract, refractive error, glaucoma, macular disease and fluctuations in glucose.
A retinal examination is needed to determine the cause.
5. How often should a person with diabetes have an eye examination?
If no retinopathy is present and diabetes is well controlled, examination every 1–2 years may be appropriate for some patients.
If retinopathy is present, examinations are generally required at least annually and often more frequently depending on severity. DOI
6. Is a retinal photograph enough?
Retinal photography can be an effective screening method, including remote interpretation and appropriate AI systems.
However, abnormal results require appropriate ophthalmologic evaluation, and retinal photography does not replace comprehensive eye care when specialist assessment is indicated. DOI
7. Are anti-VEGF injections safe?
Anti-VEGF injections are widely used and can substantially reduce vision loss from DME and PDR. They do, however, have potential ocular and systemic risks and should be administered and monitored by an appropriately trained eye-care specialist.
8. Can diabetic retinopathy disappear after blood sugar improves?
Early retinal abnormalities may stabilize and some findings can improve, but established disease does not necessarily disappear completely. Regular monitoring remains important.
9. Can people with diabetic retinopathy take aspirin?
Yes. The presence of diabetic retinopathy is not a contraindication to aspirin when aspirin is otherwise indicated for cardiovascular protection. ADA 2026 notes that aspirin does not increase the risk of retinal hemorrhage. DOI
10. Does pregnancy worsen diabetic retinopathy?
Pregnancy can accelerate preexisting diabetic retinopathy, particularly when significant retinopathy is already present. Women with preexisting diabetes should have appropriate retinal assessment before and during pregnancy. DOI
Conclusion
Diabetic retinopathy is a potentially sight-threatening complication of diabetes, but vision loss is often preventable when disease is detected early and treated appropriately.
The most effective strategy combines regular retinal screening with comprehensive diabetes management. Good glycemic control, appropriate blood pressure and lipid management, and timely referral to ophthalmology are fundamental.
For patients with vision-threatening disease, modern treatments—including anti-VEGF injections, laser photocoagulation, corticosteroid therapy and vitreoretinal surgery—can preserve or improve vision.
The most important message for people living with diabetes is simple:
Do not wait for your vision to become blurred before checking your eyes. Regular screening can save your sight.
References
- American Diabetes Association Professional Practice Committee for Diabetes. 12. Retinopathy, Neuropathy, and Foot Care: Standards of Care in Diabetes—2026. Diabetes Care. 2026;49(Suppl 1):S261-S276. doi:10.2337/dc26-S012. DOI
- American Diabetes Association Professional Practice Committee for Diabetes. Standards of Care in Diabetes—2026. American Diabetes Association. Diabetes Journals
- American Academy of Ophthalmology. Diabetic Retinopathy. EyeWiki. Updated August 2026. EyeWiki
- American Academy of Ophthalmology. Diabetic Retinopathy Screening. EyeWiki. EyeWiki
- Baker CW, Glassman AR, Beaulieu WT, et al. Effect of Initial Management With Aflibercept vs Laser Photocoagulation vs Observation on Vision Loss Among Patients With Diabetic Macular Edema Involving the Center of the Macula and Good Visual Acuity. JAMA. 2019;321:1880-1894. JAMA Network
- Bressler NM, Beaulieu WT, Glassman AR, et al. Assessment of the DRCR Retina Network Approach to Management With Initial Observation for Eyes With Center-Involved Diabetic Macular Edema and Good Visual Acuity. JAMA Ophthalmology. 2020. JAMA Network
- McAllister M, et al. Clinical practice guidelines for the treatment and management of diabetic macular oedema: a systematic review. Eye. 2025. PubMed
- International consensuses and controversies on causes, diagnosis and management of diabetic macular edema. 2025. PubMed
- Delphi Consensus on the Use of Fenofibrate as Systemic Therapy for the Prevention of Diabetic Retinopathy Progression. Journal of Diabetes. 2026. PubMed Central (PMC)
Medical disclaimer: This article is intended for education and general medical information. It does not replace an individualized examination by an ophthalmologist, optometrist, or diabetes specialist. Treatment decisions should be based on the patient’s retinal findings, visual acuity, systemic health, and local clinical guidelines.